Diabetes and Erectile Dysfunction: The Link and What Actually Helps
Why Diabetes and Erectile Dysfunction Are So Closely Linked
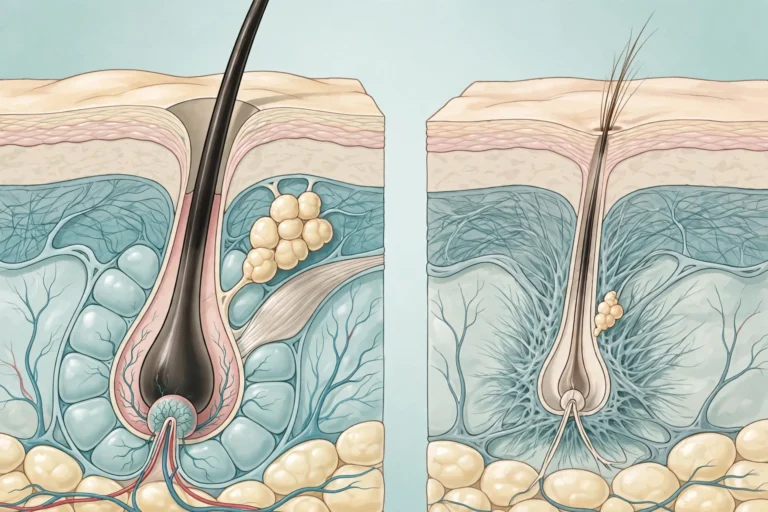
An erection is, at its core, a plumbing and wiring event. When a man becomes sexually aroused, nerve signals trigger the release of a molecule called nitric oxide inside the penis. Nitric oxide tells the surrounding arteries and smooth muscle to relax, blood rushes in, and the veins that would let blood drain out get compressed — producing an erection. This is the core reason diabetes and erectile dysfunction are so closely linked: diabetes attacks both sides of this system:
- Blood vessels (the plumbing): Chronically high blood sugar damages the endothelium, the thin inner lining of arteries that regulates blood flow. Doctors call this endothelial dysfunction. Stiffer, narrower penile arteries simply cannot deliver the surge of blood an erection requires.
- Nerves (the wiring): Diabetic neuropathy can blunt the nerve signals involved in arousal. Some men notice reduced sensation as well as weaker erections — both are consequences of the same nerve damage.
- Nitric oxide supply: Research consistently finds lower nitric oxide availability in men with poorly controlled diabetes, which means the “relax and fill with blood” signal arrives too weakly.
- Hormonal effects: Type 2 diabetes is strongly associated with low testosterone, which saps desire and compounds erection problems.
Both type 1 and type 2 diabetes can cause ED when glucose runs high over time, though type 2 is the more common culprit simply because it is more common. Problems often emerge 5 to 10 years after a diabetes diagnosis — but in some men, erection trouble appears before diabetes is ever diagnosed, making it one of the body’s earliest distress signals.
How Common Is It? The Numbers Worth Knowing
Studies estimate that 35 to 75 percent of men with diabetes will develop erectile dysfunction at some point. Men with diabetes are roughly three times more likely to have ED than men without it, and they tend to develop it 10 to 15 years earlier. Here is how the picture compares:
| Measure | What the research shows |
|---|---|
| Prevalence in diabetic men | 35–75% across studies, higher with longer diabetes duration |
| Risk vs. non-diabetic men | About 3 times higher |
| Typical age shift | ED appears 10–15 years earlier than in men without diabetes |
| Treatability | Up to 95% of cases can be treated successfully |
That last number matters most. Diabetes and erectile dysfunction may travel together, but ED is a symptom with solutions — not an inevitable price of diabetes.
ED Can Be an Early Warning Sign Your Heart Needs Attention
Here is the angle most articles skip, and it may be the most important part of this guide. The arteries supplying the penis are much smaller — roughly 1 to 2 millimeters — than the coronary arteries feeding the heart. So when high blood sugar starts damaging blood vessels throughout the body, the smallest ones often fail first. Erectile dysfunction can therefore show up three to five years before the first symptoms of coronary artery disease.
Men with diabetes are already at elevated heart disease risk, and ED may be the warning flag that goes up earliest. If you have diabetes and develop erection problems, doctors generally recommend treating it as a reason to review your cardiovascular risk — blood pressure, cholesterol, smoking, weight — not just your sex life. ED in this context is what clinicians sometimes call a “sentinel marker”: a signal to get the heart checked while there is still time to act. If you want to understand the broader landscape of causes, our guide to erectile dysfunction causes walks through how physical and psychological factors overlap.
Medications: What’s Helping, What’s Quietly Hurting
Many men with diabetes take several medications, and some of those can contribute to ED. Sorting this out is one of the highest-value conversations you can have with your doctor — because in diabetes and erectile dysfunction care, a medication review often reveals an easy win:
- Diabetes medications themselves (such as metformin) rarely cause ED directly. Keeping glucose controlled almost always helps erectile function, so stopping a diabetes drug is never the answer.
- Blood pressure drugs — particularly thiazide diuretics and some beta-blockers — are common ED contributors. Because hypertension is so frequent in diabetes, this overlap hits diabetic men hard. Our article on blood pressure medications and ED breaks down which classes are most problematic.
- Antidepressants, especially SSRIs, can affect both desire and erectile function.
- Statins have a complicated reputation here: some observational data links them to sexual side effects, but their heart-protecting benefits are usually far more important. This is exactly the kind of trade-off a doctor should evaluate with you.
One safety point deserves special emphasis: ED pills (PDE5 inhibitors) can cause a dangerous drop in blood pressure if combined with nitrate medications used for heart conditions. Because men with diabetes are more likely to have heart disease, a medication review before starting any ED treatment is not optional — it is essential. Never start, stop, or adjust a prescription on your own to fix ED.
The Testosterone Question Doctors Check Early
Low testosterone (hypogonadism) is strikingly common in men with type 2 diabetes — particularly those carrying extra weight. And it matters for a subtle reason: testosterone drives desire, while blood flow drives erection. A man with low testosterone and ED has two problems, and fixing only the plumbing may leave his libido flat.
Signs that suggest a hormone check alongside the ED workup include low interest in sex, fatigue, loss of muscle mass, mood changes, and difficulty concentrating. A simple morning blood test measures total testosterone, and if it is low, doctors may investigate the cause before deciding whether testosterone therapy is appropriate. Because diabetes and erectile dysfunction so often overlap with low testosterone, this blood test is now a routine part of the evaluation — skipping it can mean treating only half the problem.

What Actually Helps With Diabetes and Erectile Dysfunction
Treatment for diabetes and erectile dysfunction works best as a two-track plan: manage the diabetes, and treat the ED directly. Neither track alone is usually enough.
1. Better diabetes control
This is the foundation of any diabetes and erectile dysfunction treatment plan — everything else stands on it. Bringing HbA1c into target range slows the nerve and vessel damage that causes ED, and some men notice meaningful improvement. Doctors recommend a full diabetes review — medication effectiveness, diet, activity, sleep — because “tolerable” glucose control and “protective” glucose control are often different things.
2. Lifestyle changes that specifically protect erections
- Move regularly. Aerobic exercise improves blood vessel function and insulin sensitivity at the same time. Studies suggest that even modest activity — brisk walking most days — can measurably improve erectile function in men dealing with diabetes and erectile dysfunction.
- Lose excess weight. Even a small weight loss has been linked to better erections and higher testosterone in men living with diabetes and erectile dysfunction.
- Quit smoking. Smoking narrows blood vessels and lowers nitric oxide — the same molecule diabetes already depletes.
- Limit alcohol and sleep well. Heavy drinking worsens both glucose control and erections, and untreated sleep apnea (very common in type 2 diabetes) tanks testosterone and raises ED risk.
3. Oral ED medications
PDE5 inhibitors — the class that includes sildenafil, tadalafil, vardenafil, and avanafil — work for many men with diabetes and erectile dysfunction by amplifying the nitric oxide signal so more blood reaches the penis. They require sexual stimulation to work and must be prescribed, especially because of the nitrate interaction mentioned earlier. They tend to work somewhat less well when blood sugar is poorly controlled, which is another reason diabetes management comes first.
4. Second-line options when pills are not enough
For men who cannot use pills or find them ineffective, doctors may discuss alprostadil (injected into the side of the penis or used as a urethral suppository), vacuum erection devices that draw blood into the penis mechanically, and — as a last resort — surgical penile implants, which have high satisfaction rates. Low-dose daily tadalafil is sometimes used in diabetic men with both ED and urinary symptoms, at a doctor’s discretion.
5. Support for the psychological side
ED causes anxiety, and anxiety causes ED — a cycle that hits men with diabetes and erectile dysfunction hard because the physical problem is real and persistent. Counseling or sex therapy helps many couples, even when the root cause is vascular. ED-related stress can also worsen glucose control, so treating the mental side is genuinely part of treating the diabetes side.
How to Talk About It — With Your Doctor and Your Partner
Most men delay this conversation for months or years, and partners often misread the silence as lost interest. Doctors who treat diabetes hear about ED constantly — raising it is unremarkable to them and changes your care plan immediately. Health authorities including the CDC stress that these problems are often treatable and worth discussing openly. Try: “I’ve been having trouble with erections, and I’d like to understand whether my diabetes is involved and what we can do about it.”
With your partner, the clinical framing helps: the connection between diabetes and erectile dysfunction is a blood-vessel and nerve issue, not a verdict on attraction. Couples who discuss it openly tend to adapt better — exploring other forms of intimacy while treatment takes effect — than couples who let it become the thing nobody names. And if your partner has noticed changes too, bringing them into the doctor conversation can turn a source of tension into a shared health project.
FAQs
Can diabetes cause permanent erectile dysfunction?
Diabetes can cause long-lasting ED, but “permanent” is rarely the right word for diabetes and erectile dysfunction. While years of high blood sugar can produce nerve and vessel damage that is difficult to fully reverse, up to 95% of cases respond to some treatment — from better glucose control to oral medications, injections, vacuum devices, or implants. Early treatment protects the most function, so seeing a doctor sooner gives you more options.
Will lowering my blood sugar improve my erections?
Often, yes — at least partially. Better glucose control slows further nerve and vessel damage, and studies link tighter control with better erectile function. Oral ED medications also tend to work better when blood sugar is well managed. Think of diabetes control as the foundation: it may not erase existing damage, but it stops the decline and makes every other treatment more effective.
Are Viagra or Cialis safe if I have diabetes?
For most men with diabetes, yes — but the decision belongs to a doctor. PDE5 inhibitors are commonly and effectively prescribed for diabetic men, and clinical guidance on diabetes and erectile dysfunction supports them as first-line treatment when safe. The critical exception is men taking nitrates for heart conditions, where the combination can cause a dangerous blood pressure drop. Your doctor will review your heart health and medication list before prescribing.
Can erectile dysfunction be the first sign of diabetes?
Yes. Erection problems sometimes appear before diabetes is diagnosed, because the small penile arteries can be damaged by rising blood sugar earlier than symptoms like thirst or fatigue emerge. This is one reason the combination of diabetes and erectile dysfunction deserves attention in both directions: ED in a man with risk factors is a prompt for a diabetes screening, and new ED in a man who already has diabetes is a prompt to check how well the disease is controlled.
I am young and have type 1 diabetes — why is this happening to me?
ED is not only a middle-age problem. In type 1 diabetes, long-term glucose exposure can damage nerves and vessels even in younger men, and the psychological weight of a chronic condition adds to the risk. It does not mean your diabetes is out of control, but it does deserve a doctor’s attention. Treatment options work the same way at any age, and starting early preserves the most function.
Should my partner come to the doctor’s appointment?
It can help. ED affects both people in a relationship, and many doctors welcome partners because treatment works better when expectations are aligned. Some couples find counseling useful for the frustration and performance anxiety that build up around ED. At minimum, being honest with your partner that this is a medical issue — not a loss of interest — protects the relationship while you pursue treatment.
Medical disclaimer: This article is for educational purposes only and is not medical advice. Erectile dysfunction can signal underlying health conditions such as diabetes or heart disease. Always consult a qualified healthcare professional for diagnosis and treatment — do not start, stop, or change any medication without your doctor’s guidance.